

From 10 NHS PAs to eight

You would like a less crowded NHS week, but the pension gives you pause. If you reduce from ten programmed activities, or PAs, to eight, will the pension you have spent decades building fall by a fifth too?
Not automatically. Benefits already built up in the 1995 or 2008 Section need assessing separately from future pension earned in the 2015 Scheme. A simple percentage of current salary cannot describe the whole effect.
There is another question alongside the calculation: what would the revised job plan actually release? A reduction on paper is useful only if the agreed commitments and timetable deliver the change you want.
This guide concerns hospital consultant officer members of the NHS Pension Scheme in England and Wales. Scotland and Northern Ireland have separate schemes. Job-plan arrangements need agreement with the employer.
Begin with the working week you want
Put the current and proposed job plans side by side. Identify which clinics, lists or other direct clinical care sessions would stop, and what would happen to the patient-related administration attached to them.
Then examine supporting professional activities, on-call commitments, travel and other responsibilities. Consultant job-planning guidance distinguishes the different components of the role. The practical question is where each remaining commitment would sit in the new timetable.
Would eight PAs create a reliable free day, shorter working days or gaps that are difficult to use? Which arrangement would preserve the NHS work you value while reducing the pressure you want to change?
Decide what the released time is intended for. Moving a private clinic out of an evening could improve family life without reducing private work. Leaving the time unfilled could provide recovery or room for other interests. Filling it with additional private sessions is a separate choice with its own costs and workload.
Separate existing benefits from future accrual
For officer members, 1995 and 2008 benefits use pensionable membership and a final salary measure. NHSBSA explains that reducing hours does not reduce membership already built up, and that the legacy pay measure uses whole-time equivalent pay.
Working eight PAs at the same whole-time pay rate is therefore different from taking a lower-paid role. Your actual pay falls, but the equivalent full-time rate need not.
Where retained, the final salary link connects legacy benefits to pay at retirement. Check service history, breaks and pay components rather than assuming that being at the top increment settles the position. The 1995 and 2008 Sections closed to further accrual on 31 March 2022; new benefits are now earned in the 2015 Scheme.
Calculate the smaller slice earned each year
The 2015 Scheme uses actual pensionable earnings, with an accrual rate of 1/54th. Lower earnings mean a smaller new slice of annual pension, with subsequent revaluation. They do not retrospectively cut every slice already earned.
For illustration, assume pensionable pay falls proportionately from £120,000 at ten PAs to £96,000 at eight, with no other changes. These are hypothetical figures, not a consultant pay scale.
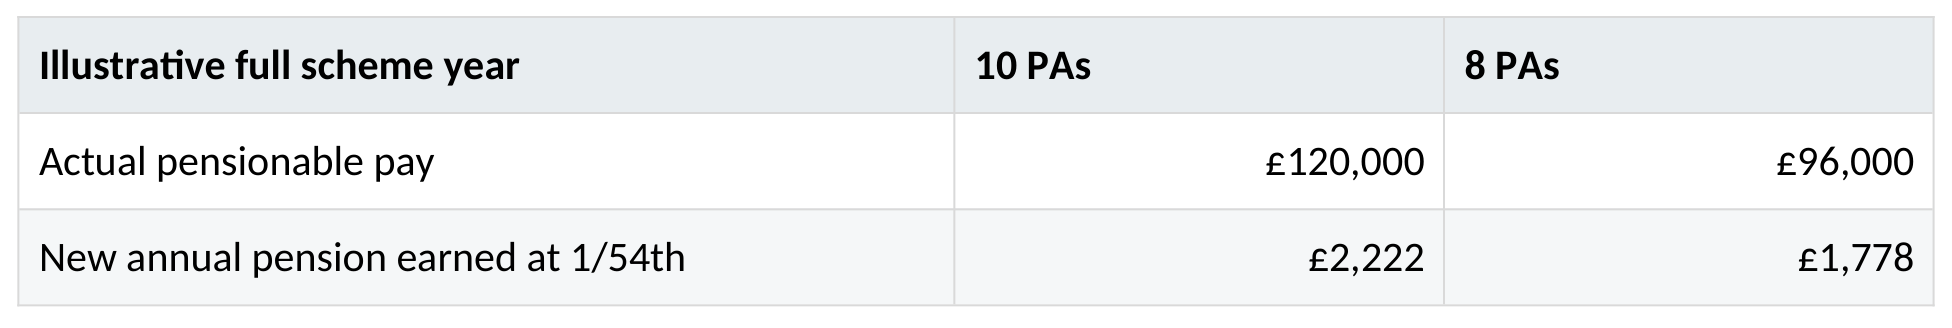
The difference is around £444 of annual retirement income for each full year worked on the lower pay, before subsequent revaluation and any early-retirement adjustment. It is not a £444 reduction in monthly salary. A projection should allow for each year of the proposed pattern.
Compare household income after deductions
A 20% reduction in gross NHS pay is not necessarily a 20% reduction in household spending money. Income Tax, National Insurance and pension deductions change too. Private income and your wider tax position affect the result.
Ask for annual and monthly comparisons after those deductions, using the actual proposed pay. If more private work is contemplated, include fees, costs that change, additional administration and the personal proceeds after tax. Company turnover or retained cash cannot simply be added to household income.
Set the resulting income against current commitments and the reserves you want to retain. The comparison should show the cost of a workable timetable, including the time outside paid sessions.
Check partial retirement against the later timetable
Different scheme sections have different normal pension ages: normally 60 for 1995 benefits, 65 for 2008 benefits, and State Pension age or 65, whichever is later, for 2015 benefits. Earlier payment can reduce benefits.
Partial retirement can allow eligible members to draw pension while continuing NHS work and earning further 2015 benefits. It requires an agreed arrangement and at least a 10% reduction in actual pensionable pay, maintained for at least 12 months. The reduction is assessed against pensionable pay in the preceding 12 months, alongside the other eligibility requirements.
Reducing to eight PAs at 58 does not automatically meet that test for partial retirement at 60. A further change may be needed, depending on the actual pay and timing. Obtain estimates showing which benefits would be drawn, when, and with what adjustments. If McCloud applies, include the remedy choice in the assessment.
Compare the arrangements you could sustain
Model continuing at ten PAs, reducing to eight with the same retirement date, and reducing now while remaining in medicine longer. Partial retirement may form part of a route if the conditions are met.
For each, show spendable income, pension at the relevant dates, savings needed to bridge any gap and the actual working week. Include your partner’s timetable and the effect on the people and commitments that matter to you.
Then take the proposed job plan to the employer and the financial comparison to your partner. A smaller future accrual may be a price you are comfortable paying for a better week. The useful answer is the cost of that particular change, what it releases and whether it supports a way of working you want to keep.
This article provides general information, not individual pension or financial advice. Scheme benefits, job plans and tax treatment depend on your circumstances. The pay illustration is hypothetical. Rules were checked on 26 October 2026.
Let’s talk about what matters to you
An initial conversation, at no cost to you.

London
EC2A 2BX


Ralated Blogs
Copy here introducing the client stories section and examples of testimonials
Your company can change without you investing another penny

Check NHS pension growth before your company contributes
How should you use your private practice profits